Inside Cardinal’s In-Clinic ABA Therapy Services

Inside Cardinal’s In-Clinic ABA Therapy Services


Our BCBA Alice Okamoto walks through a day in our ABA clinics, what a clinic can do that home can't, and why it isn't daycare.
October 20, 2026
 
6 min read
Dr. Mike Henderson
Regional Operations Director @ Cardinal Pediatric Therapies
Mike Henderson, PhD, LBA, BCBA-D, is the Regional Operations Director at Cardinal Pediatric Therapies. With over two decades of experience in behavior analysis and organizational leadership, he focuses on mentoring teams and fostering a culture of collaboration, growth, and excellence in client care.
In conversation with
Alice
MA, BCBA, LBA, Chief of Staff @ Cardinal Pediatric Therapies
Alice has spent more than six years at Cardinal, supervising behavior analyst trainees and working with families as a whole unit. She first worked with ABA as a teenager, supporting twins with autism at home and later at school.
In-Clinic ABA Therapy Services

In-clinic ABA therapy services give your child a predictable day in a space set up for learning.

There’s a daily schedule, a fun start with their therapist, focused time on goals, and social practice like group games and lunch with other kids. And it’s a medically indicated, insurance-funded service. Not daycare.

Alice Okamoto, a BCBA and Cardinal’s Chief of Staff, explains how Cardinal’s clinics work and answers the worry parents bring up most.

Key takeaways

  • Lunch and group games are part of the therapy, not a break from it.
  • Clinic rooms get set up around what each child is working on.
  • For some kids, that structure means picking up new skills faster.
  • Peers and other adults in the clinic help new skills carry over to everyday life.
  • Every hour works toward goals in your child’s plan, which is what makes it therapy and not daycare.

Clinic or Home: Where Families Start

Maybe you’ve booked a clinic tour and you’re still reading up on in-home ABA therapy. Totally normal. Cardinal offers both as part of its ABA therapy services, and the right one depends on your kid, not on which one sounds better.

What usually decides it:

  • Your child’s age and goals. A BCBA recommends a setting after assessing your child.
  • Whether your child needs practice with other kids.
  • How busy your house is during the hours therapy would happen.
  • Your family’s schedule.

If a clinic is on your list, here’s what the day looks like and why it works so well for some kids.

What a Day of In-Clinic ABA Therapy Looks Like

A day of in-clinic ABA therapy at Cardinal runs on routine: your child arrives, starts with something fun alongside their therapist, works on the goals in their plan, then joins group games and lunch with other kids. Kids walk in to the same routine every day, and that’s on purpose.

“We try to really create as much routine and consistency as possible.”
Alice Okamoto

The details shift with your child’s age and goals. Most days move through four parts:

  • Arrival. Belongings go away, the same way every time.
  • Pairing. The day opens with something fun with the therapist. Alice calls it “starting the session off in a fun and engaging way,” and it keeps the relationship strong before any work starts.
  • Goals. Then it’s into the goals written into your child’s program, with data taken as they go.
  • Group time. Social skills practice, like a group game, and lunch together with other kids.

That last part is hard to copy at home. Lunch with friends is therapy too. It just doesn’t look like it.

What a Clinic Can Do That's Harder at Home

A clinic can do two things that are harder at home: therapists can set up the room so your child’s target skill keeps coming up, and they can keep out everyday distractions. We asked Alice what a clinic offers that home doesn’t. Her first answer was control over the room.

“We’re able to really manipulate the environment to contrive opportunities for running goals and working on the program the best that we need to.”
Alice Okamoto

Put simply, therapists can arrange a room so the skill your child is working on keeps coming up. Some clinic rooms are even set up like a classroom, with the kind of structure you’d see in preschool classroom activities for kids with autism.

The other half of her answer was about what a clinic leaves out. At home, therapy shares the space with:

  • The TV on in the next room for a sibling
  • Parents coming in and out
  • The dog barking

None of that means something is wrong with your home. In Alice’s words, “It’s just all very natural things that happen at home. And we’re able to limit, obviously, some of those things in the clinic.” For a child learning something brand new, every interruption is a chance to practice that gets lost.

Clinic-Based ABA Therapy

Why Structure Helps Some Children Learn

Structure helps some children learn because a predictable day leaves more time and attention for practice. With fewer surprises and interruptions, a child gets more repetitions on each goal. Asked what all that structure gives a child, Alice didn’t hesitate: “the potential to be able to pick up new skills, maybe faster.”

A kid who knows what comes next isn’t spending the morning watching the door, so more of the day goes to learning. Alice listed what a structured clinic day adds:

  • More repetition
  • More consistency
  • More of the routine and schedule worked through
  • More of the goals and targets reached each session

Hours matter too. A National Research Council report set a recommended weekly minimum of intervention for young children with autism (National Research Council, 2001).

25 hours
Recommended weekly minimum, year-round

That’s a guideline, not a prescription. Your child’s BCBA recommends hours after an assessment, so the right number for your child may be different.

Wondering what a clinic day would look like for your child? Talk with our team and we’ll walk you through it.

Center-Based ABA Therapy

Does In-Clinic Mean Less Individual Attention?

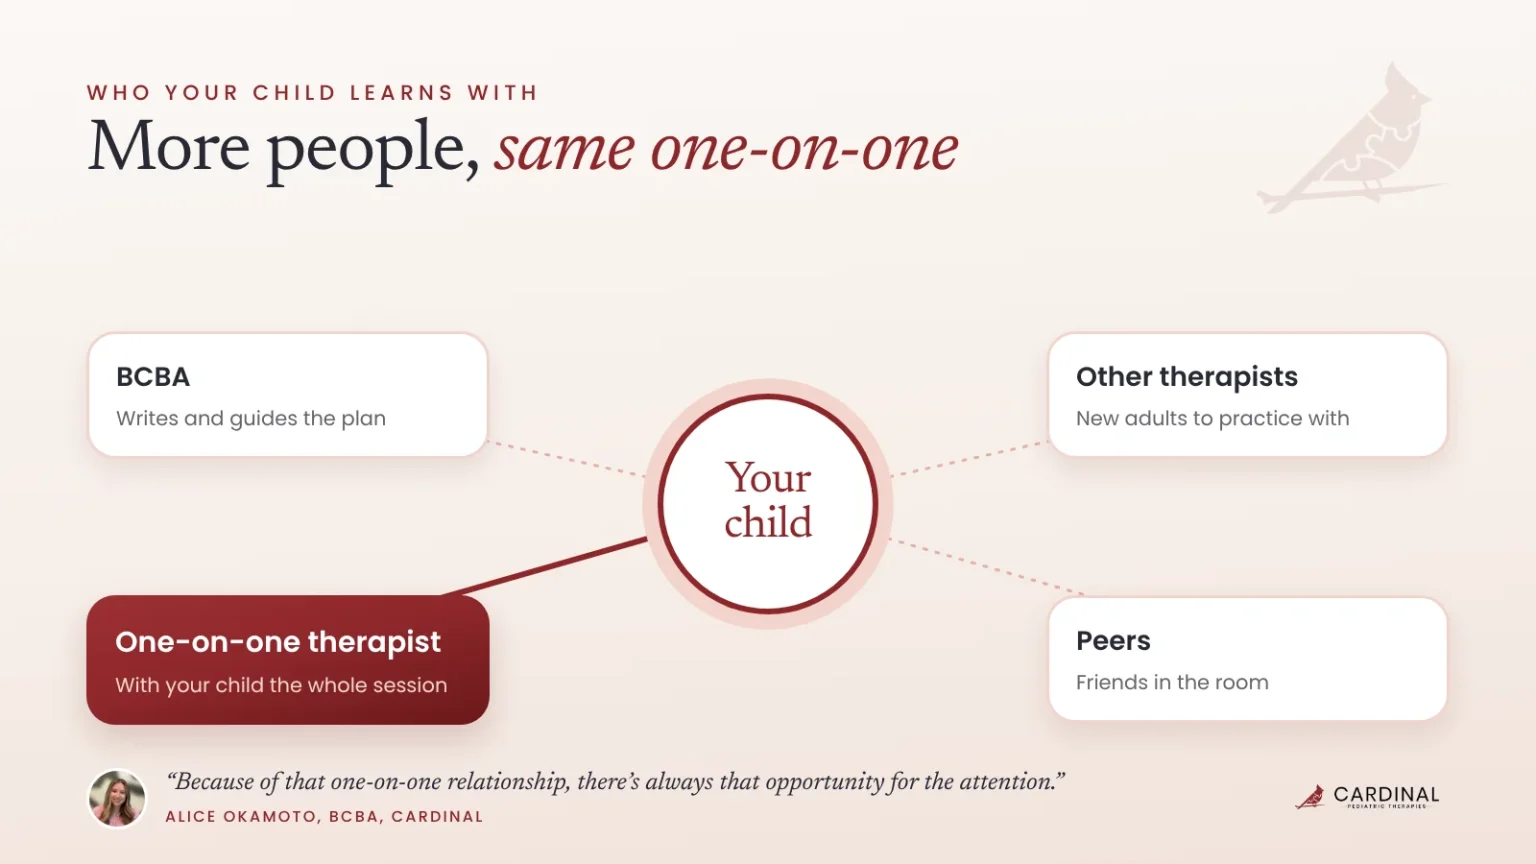
No. Most children in Cardinal’s clinics still have their own one-on-one therapist for the whole session, and that therapist stays focused on your child’s goals. It’s a fair worry, since more kids in the building can sound like less time for yours. Alice’s answer is short.

“So most of our clients do have the one-on-one therapist... they’re getting that one-on-one attention throughout their session and throughout their day.”
Alice Okamoto

A clinic adds people to your child’s day. It doesn’t take away the one-on-one ABA services at the center of every session.

Those extra people turn out to be useful. Alice pointed to “opportunities to provide generalization to other adults, more peers.” Generalization means a skill your child learned with one person shows up with other people and in other places too. In practice, that’s a skill being used:

  • With a different adult, not only their own therapist
  • With peers, during group games and lunch
  • Back home, during family time and playdates

A skill that only works with one person in one room isn’t finished yet. A clinic gives it more places to get tested.

ABA Clinic

In-Clinic ABA Is Not Daycare

In-clinic ABA is not daycare because every hour works toward goals in your child’s treatment plan, with data taken and progress reviewed by a BCBA. Alice is kind about this one. She gets why it can feel that way. Parents want to know their child is “in a safe environment with people that they trust.”

But, as she put it, “we are much more than daycare and babysitting.”

What makes it therapy, according to Alice:

  • It’s an insurance-funded, medically indicated service.
  • It needs consistency in services, so your child keeps building on the last session.
  • It depends on “communication and transparency with parents, school teams, other related providers.”

At Cardinal, your child’s goals and progress get reviewed every six to twelve weeks. In Alice’s words, kids in the clinic “are working on really, really important things throughout their day at therapy.”

In-Clinic ABA Therapy Services at Cardinal

Cardinal offers in-clinic ABA therapy services in four clinics across North Carolina and Arizona, each set up for structured learning and group practice, and every child there has a BCBA guiding their plan and a therapist working with them directly. Here’s what that looks like across our locations:

  • Clinics: Cary, Clayton and Wilmington, North Carolina, and Phoenix, Arizona
  • The team: BCBAs, RBTs and specialists trained in early childhood and autism
  • Getting ready for school: the Classroom Readiness Program
  • Rather stay home? In-home ABA therapy is an option too

Each clinic’s address is listed on our in-clinic ABA therapy page.

Thinking about a clinic for your child? Call (919) 705-0668 and we’ll help you figure out if it’s the right fit. No pressure, just answers.

Get started
→

Frequently Asked Questions

Center-based ABA therapy, also called in-clinic or clinic-based ABA, is ABA delivered at a therapy center instead of at home. Your child follows a daily routine with a trained therapist, works on goals from their treatment plan, and practices social skills with peers in rooms set up for learning.

At Cardinal, your child’s goals and progress get reviewed every six to twelve weeks. The BCBA looks at the session data, updates goals your child has met, and adjusts anything that isn’t working, so the plan keeps up with your child as they grow.

Often, yes. Some kids get their therapy at the clinic while parent training happens at home. Alice told us the team stays flexible about “going in home and also working with parents in that natural environment.” What’s possible also depends on your plan and your BCBA’s recommendation.

Cardinal has ABA clinics in Cary, Clayton and Wilmington, North Carolina, and Phoenix, Arizona. If a clinic isn’t close by, in-home and community ABA is available across North Carolina, Arizona and Texas, so your child can still get care in the setting that fits your family.

Often, when ABA is medically necessary. Plans differ on what they cover, including which settings and how many hours. Cardinal can give you a quote of benefits so you know what your plan covers, and what you might owe, before your child starts.

In this article
Want to see one of our clinics?
Dr. Mike Henderson
Regional Operations Director @ Cardinal Pediatric Therapies
Mike Henderson, PhD, LBA, BCBA-D, is the Regional Operations Director at Cardinal Pediatric Therapies. With over two decades of experience in behavior analysis and organizational leadership, he focuses on mentoring teams and fostering a culture of collaboration, growth, and excellence in client care.
Alice
In conversation with
MA, BCBA, LBA, Chief of Staff @ Cardinal Pediatric Therapies
Alice has spent more than six years at Cardinal, supervising behavior analyst trainees and working with families as a whole unit. She first worked with ABA as a teenager, supporting twins with autism at home and later at school.

Related posts

In-Clinic ABA Therapy Services
ABA Therapy
ABA Therapy
Inside Cardinal’s In-Clinic ABA Therapy Services

Our BCBA Alice Okamoto walks through a day in our ABA clinics, what a clinic can do that home can't, and why it isn't daycare.
Types of ABA Therapy
ABA Therapy
ABA Therapy
Types of ABA Therapy: Which one is right for your child?
Applied Behavior Analysis (ABA) therapy is a highly effective form of therapy for children with Autism Spectrum Disorder (ASD) and other developmental disabilities.
Questions to Ask before Choosing an ABA Therapist
ABA Therapy
ABA Therapy
Questions to Ask Before Choosing an ABA Therapist for Your Child
If you’re wondering what Questions to ask before choosing an ABA Therapist for your child, you’ve come to the right place.
Want to see one of our clinics?​

What One-on-One ABA Services Actually Look Like

What One-on-One ABA Services Actually Look Like

Our BCBA Alice Okamoto explains what happens in a one-on-one ABA session, who it fits best, and what to expect in the first weeks.
October 6, 2026
 
5 min read
Dr. Mike Henderson
Regional Operations Director @ Cardinal Pediatric Therapies
Mike Henderson, PhD, LBA, BCBA-D, is the Regional Operations Director at Cardinal Pediatric Therapies. With over two decades of experience in behavior analysis and organizational leadership, he focuses on mentoring teams and fostering a culture of collaboration, growth, and excellence in client care.
In conversation with
Alice
MA, BCBA, LBA, Chief of Staff @ Cardinal Pediatric Therapies
Alice has spent more than six years at Cardinal, supervising behavior analyst trainees and working with families as a whole unit. She first worked with ABA as a teenager, supporting twins with autism at home and later at school.
One-on-One ABA Services

One-on-one ABA services pair one trained therapist with one child for the whole session.

Sessions start with something fun to build trust, then move through the child’s schedule and their own goals: communication, social skills, daily living. It’s medically indicated therapy, with goals sent to insurance.

Whether it’s the right fit comes down to your child’s age and goals, and progress takes time.

Key takeaways

  • One-on-one ABA means one therapist working on one child’s goals for the whole session.
  • Every session starts with pairing, a fun stretch that builds trust before any goal work.
  • Every child’s plan is written by a BCBA and built from an assessment.
  • Younger kids often do best one-on-one. Teens working on friendships may fit a peer group better.
  • Progress comes in small steps, so the early weeks can look like a lot of play.

Why Families Ask About One-on-One ABA

For a lot of families, the ABA recommendation shows up in a stack of diagnosis paperwork. What it means for an ordinary weekday at home or at the clinic tends to get skipped. Families want to know who will be in the room, what their child will do, and whether it will help.

You’re in big company. Autism is common, and the CDC tracks how often it is identified in U.S. children.

1 in 31
Children identified with autism by age 8
And ABA is often one of the first services families hear about. The American Academy of Pediatrics lists ABA-based interventions among the evidence-based options for children with autism (AAP clinical report, Pediatrics, 2020).

Numbers don’t tell you what a session feels like, though. So we sat down with Alice Okamoto, a BCBA and Cardinal’s Chief of Staff. She’s spent more than six years helping families get started with ABA therapy services.

What One-on-One ABA Services Mean

One-on-one ABA services mean one trained therapist works with one child for the whole session, following a plan written for that child and nobody else. At Cardinal, therapists hold certifications such as Registered Behavior Technician (RBT) and Board Certified Behavior Analyst (BCBA), and each child’s plan is written by their BCBA.

It sounds simple, and it mostly is. But “one-on-one” makes some parents picture a sitter watching their kid play. When we asked Alice what parents get wrong most, she didn’t hesitate: people think it’s babysitting. “We hear that a lot,” she said.

Here’s what’s actually going on in a session:

  • It’s medically indicated. ABA is recommended because of your child’s specific needs, not as a place to drop them off.
  • It runs on goals. As Alice puts it, “we’re working on things and goals that we send to insurance.”
  • Progress gets measured. Therapists track data on each goal every session, and when something isn’t working, the plan changes.

Babysitting doesn’t come with data sheets.

One-on-One ABA Therapy Services

What Happens in a One-on-One ABA Session

A one-on-one ABA session at Cardinal follows a predictable pattern: the same arrival routine, a fun warm-up called pairing, then focused time on your child’s goals. Kids do better when they know what’s coming, so the start stays the same every time. Then the day unfolds from there.

Alice explains why it starts with play.

“Usually we try to start a therapy session with what we call pairing... Doing something fun, doing something engaging.”
Alice Okamoto

In practice? Blocks, bubbles, whatever your child is into.

The setting matters some. In-clinic ABA therapy mixes group games and lunch with other kids into a typical clinic day. In-home ABA therapy works around whatever’s going on at your house, siblings and the dog included.

The basic routine doesn’t change.

Step What it looks like
1. Arrival Belongings away, same routine every time
2. Pairing A fun activity with the therapist to build trust
3. The day's schedule Group readiness work, snack, lunch, play and social time
4. Individual goals Focused time on the goals in your child's plan
5. Consistency Sessions look similar day to day, with room to adjust

Skills Children Build in One-on-One ABA

Children in one-on-one ABA build the skills they need most at home, at school and with friends, starting with communication. “We do so many things,” Alice told us. But communication comes first, and she says it carries into “really everything else too.”

A child who can ask for a break has an easier time with every other goal on the list, which is why building communication skills usually comes first. From there, sessions usually include:

  • Social skills, like turn-taking and joining play
  • Daily living skills, from routines to self-care
  • Fewer challenging behaviors, when that’s part of the plan

No two programs match. Your child’s BCBA builds goals from an assessment of where your child is right now.

For kids heading toward school, Cardinal’s Classroom Readiness Program takes those same skills and practices them in a small group.

Why One Therapist for One Child Matters

The biggest benefit of one-on-one ABA is trust. When one therapist works with your child session after session, your child learns that person is safe, and new skills get easier to try. We asked Alice for the biggest benefit, and her answer wasn’t about skills at all.

“When they’re able to build that rapport, it’s easier for the child to... trust that that therapeutic relationship is there.”
Alice Okamoto

A child who has met someone twice acts differently around them than a child who knows that person well. One-on-one gives the therapist enough time with your child to get to the second stage, and a few things follow from that:

  • Your child tries new things more easily
  • The therapist picks up on your child’s cues, like when frustration is starting to build
  • There’s no group to wait on, so teaching can happen right when the moment comes up

Curious what a session would look like for your child? Talk with our team, and we’ll walk you through it on a short call.

Is One-on-One ABA Right for Every Child?

Not always. One-on-one ABA tends to fit younger children building their first skills, while some teens do better in a social skills group with one therapist and a few peers. The right format depends on your child’s age and goals, and a BCBA recommends it after an assessment.

1 on 1 ABA Therapy

Alice is refreshingly direct about it. For younger kids, she says one-on-one is “very beneficial.” Teens working on friendships often get more out of practicing with peers, so the format shifts as a child grows.

That’s also why starting early matters, and a big reason families ask about the best age to start ABA. These are the milestones the CDC points to:

18 months
First recommended autism screening
Age 2
When a diagnosis can be reliable
47 months
Typical age kids are diagnosed

Hours depend on the child too. National guidelines split ABA into two rough types (CASP ABA Practice Guidelines, 2024), and the right number of hours of ABA therapy a week comes out of your child’s assessment.

Program type Typical weekly hours Usually for
Focused ABA About 10 to 25 hours A few specific goals
Comprehensive ABA About 30 to 40 hours Goals across many skill areas

What to Know Before the First Session

Before the first session, know that progress takes time. Most of the first two weeks go to pairing, so your child’s therapist is building trust through play before diving into program goals. Progress tends to come in small steps rather than a straight line, and that’s normal.

“Progress is not immediate. It does take time, and it’s really worth trusting the process.”
Alice Okamoto

Cardinal focuses on rapport “for like two weeks before diving into some of the program goals,” Alice says. And her description of progress is the most honest one we’ve heard: “little nuggets here and there instead of very linear.”

So if the first two weeks look like a lot of play, that’s the point. The relationship comes first.

ABA Therapy Services

One-on-One ABA Therapy Services at Cardinal

Cardinal offers one-on-one ABA therapy services in clinics, at home and in the community, and every child gets a BCBA guiding their plan plus a therapist who works with them directly, session after session. Where that happens is up to your family:

  • In the clinic: Cary, Clayton and Wilmington, North Carolina, and Phoenix, Arizona
  • At home and in the community: across North Carolina, Arizona and Texas
  • Getting ready for school: the Classroom Readiness Program

Our tagline is “Families first.” In practice that means if the schedule stops working for you, or a goal doesn’t line up with what matters at home, we change it.

Wondering whether one-on-one is right for your child? Call (919) 705-0668. No commitment, just a conversation.

Get started
→

Frequently Asked Questions

A Board Certified Behavior Analyst (BCBA) does. The BCBA writes your child’s treatment plan, trains and supervises the therapist who runs each session, reviews the data, and updates goals as your child progresses. That supervision is what makes one-on-one ABA structured treatment rather than general childcare.

Pairing is how a therapist earns a child’s trust before teaching anything new, mostly through play the child already loves. It opens every session and carries the most weight early on, so your child sees the therapist as someone safe and fun before goal work begins.

It depends on your child. A BCBA recommends hours after an assessment, based on age, goals and setting. National practice guidelines put focused programs around 10 to 25 hours a week and comprehensive programs around 30 to 40, and hours can change as your child progresses.

Often, when it’s medically necessary, though coverage, copays and approved settings vary by plan. Cardinal can walk you through a quote of benefits before you start, so you know what your plan covers, how many hours are approved, and what you might owe.

At Cardinal, one-on-one ABA can happen in a clinic, at home or in the community. Clinics are in Cary, Clayton and Wilmington, North Carolina, and Phoenix, Arizona, with home and community sessions across North Carolina, Arizona and Texas. A BCBA helps your family choose the setting that fits your child’s goals.

In this article
Not sure if one-on-one fits your child?
Dr. Mike Henderson
Regional Operations Director @ Cardinal Pediatric Therapies
Mike Henderson, PhD, LBA, BCBA-D, is the Regional Operations Director at Cardinal Pediatric Therapies. With over two decades of experience in behavior analysis and organizational leadership, he focuses on mentoring teams and fostering a culture of collaboration, growth, and excellence in client care.
Alice
In conversation with
MA, BCBA, LBA, Chief of Staff @ Cardinal Pediatric Therapies
Alice has spent more than six years at Cardinal, supervising behavior analyst trainees and working with families as a whole unit. She first worked with ABA as a teenager, supporting twins with autism at home and later at school.
Not sure if one-on-one fits your child?

School-Based ABA Therapy: How It Compares to Other Delivery Models

School-based ABA therapy means a behavior analyst or technician works with a child right inside their classroom, alongside their teacher. It’s one of four common ways ABA gets delivered; the others are center-based, in-home, and a hybrid of the two.

No single model is automatically the best fit for every child. In practice, what your school district and insurance plan offer often matters as much as which model works best in theory.

What does “School-Based ABA Therapy” Mean?

At its simplest, school-based ABA means a therapist works with your child in their actual classroom, in real time, as the school day happens.

How that plays out varies a lot by district. Some districts build a therapist into a child’s IEP as a related service under federal special education law. Others only allow limited coordination with an outside provider. And many families can’t get daily in-classroom support at all, even if they’d prefer it.

Our guide to ABA therapy in schools goes deeper into what this looks like in practice, including why Cardinal doesn’t place therapists in public school classrooms daily and what our clinic-based alternative offers instead.

This article stays focused on how school-based therapy compares with the other delivery options families are usually weighing.

Consider a family whose child does well with predictable routines but struggles with transitions, group activities, and following classroom-style instructions. The family may initially consider receiving ABA support in the child’s everyday school environment because practicing skills where challenges occur can help connect therapy to real-life routines.

At the same time, they may consider center-based ABA because a structured clinic environment can reduce distractions while providing opportunities to practice communication, social interaction, self-regulation, transitions, and other school-readiness skills with professional support and peer interaction.

Ultimately, the delivery setting should reflect the individual child’s needs, preferences, goals, and the environments where support is most useful.

How School-Based Compares to Center-Based and In-Home ABA

Each delivery model is different on a few consistent factors:

  • Peer interaction and generalization. School-based ABA has a natural advantage here; skills get practiced directly in the setting where a child ultimately needs to use them, alongside real peers. Center-based programs try to recreate that in a structured group setting; in-home therapy has the least built-in peer interaction.
  • Consistency of oversight. A school-based therapist usually splits their time across several students and has to work around the teacher’s schedule. Center-based and in-home therapists don’t face that constraint, so their sessions tend to be more consistent and more individualized.
  • Family involvement. In-home ABA involves parents the most, since sessions happen right in your family’s daily routine. With school-based or center-based ABA, you’re more likely to get progress reports and periodic check-ins than day-to-day coaching.
  • Access and logistics. School-based access depends on your district’s policies and the IEP process, which is mostly outside your control. Center-based and in-home therapy are usually easier to arrange because you can set that up directly with your provider.

No model is better across the board. The right one depends on what your child needs most, and on what your district and insurance plan actually make available.

Why Many Families Prefer a Hybrid Approach

Most families don’t stick to just one model. An easier approach would be  to start with clinic-based or in-home ABA to build core skills like communication, following instructions, and transitions.

When those skills are solid, you can coordinate with the school team to help them carry over into the classroom.

This is close to how Cardinal works. Our in-clinic ABA therapy program we build classroom-relevant skills in a structured setting. We share progress with families, and when it makes sense, we coordinate directly with your child’s school team rather than sending a therapist into the classroom.m 

How to Decide Which Model Fits Your Child

Some questions tend to matter more than which model sounds best in the abstract:

  • What does your district or insurance plan actually offer? This can narrow your real options.
  • What is your child working on right now? Foundational skills like communication or following instructions are easier to build in a lower-distraction setting, before generalizing to a classroom.
  • How involved do you want to be day to day? In-home ABA gives you the most built-in coaching. School-based and center-based therapy give you less by default.

If classroom skills are the goal right now, our Classroom Readiness program is worth a look. No matter which long-term model you choose it’s built specifically to bridge therapy work into real classroom readiness.

Talk Through Which Model Makes Sense for Your Child

There’s no single right answer here. The best delivery model depends on your child’s goals, your district’s policies, and what your family can realistically keep up day to day. Cardinal Pediatric Therapies can walk you through how our clinic-based model compares to the school-based options in your district.

Contact our team to determine which approach best fits your child.

What does “school-based ABA therapy” mean? 

School-based ABA means a behavior analyst or technician will work inside your child’s classroom. What could be available varies a lot by school district, insurance plan, and provider, so one family’s options can look very different from another’s.

Is school-based ABA better than center-based ABA?

Neither one is better than other. School-based ABA lets your child practice skills directly with real classmates. Center-based ABA  offers a more consistent, one-on-one therapist time in a quieter setting. Which one’s right depends on your child’s specific goals and what your district actually offers.

Does insurance cover school-based ABA therapy? 

It depends on your insurance plan and your school district’s policies. School-based services are often set up through the IEP process rather than billed the same way as clinic or in-home ABA.

Can ABA therapy happen both at a center and in school? 

Yes, families like to chose the hybrid approach. Many families start with clinic-based or in-home ABA to build core skills, then bring the school team in once those skills are ready to carry over into the classroom, rather than picking just one model and sticking with it.

How do I know if my child needs school-based ABA specifically? 

If your kid can handle classroom routines and just needs help carrying some specific skills into school, school-based coordination would be a great option. If  skills like communication or following instructions still need work, a quieter, clinic-based or in-home setting is usually a more efficient place to start.

Calming Sensory Activities for Autism: What to Try in the Moment

When a child with autism is overwhelmed, the sensory techniques that help most are different from the general sensory activities used for everyday play.

Deep pressure a firm hug, a weighted blanket, or compression is one of the most consistently supported in-the-moment calming techniques, alongside slow rhythmic movement and reducing competing sensory input.

The right technique depends on the individual child’s sensory profile, and it works best when you identify and practice it before overwhelm, not when you try it for the first time during one.

How to Recognize Early Signs of Sensory Overload

If we catch overload early, it makes calming techniques more effective. A few common early signs to watch for:

  • Covering their ears or eyes, even in response to sounds or lights that don’t seem loud or bright to an adult.
  • Increased stimming, frequent or intense repetitive movements than usual.
  • Pacing, fidgeting, or restlessness that wasn’t present a few minutes earlier.
  • Withdrawal or going quiet, which can look like calm but is sometimes an early overload sign rather than the absence of one.

Every child’s early warning signs look a little different, so learning your own child’s specific pattern matters more than any general checklist.

We have noticed that one of the main overload signs that we can find is fidgeting and covering their ears. At this point, we at Cardinal recommend starting with any calming technique as soon as possible. 

Deep Pressure and Proprioceptive Calming Techniques

Deep pressure is among the better-studied calming techniques for autism specifically. Research on deep pressure input has found it produces a calming effect on the autonomic nervous system, with one study reporting a measurable reduction in anxiety and arousal among children with autism.

A pilot study using a short-term deep-pressure portable seat found measurable improvements in behavioral ratings after repeated brief sessions.

Some easy ways to apply deep pressure in the moment:

  • A firm hug or compression, if the child seeks and consents to physical touch; not every child does, and this should never be forced.
  • A weighted blanket or lap pad, applied for a few minutes rather than left on indefinitely.
  • Wall pushes or resistance activities, which provide proprioceptive input through the joints and muscles without requiring physical contact from another person.
  • Tight swaddling or a compression vest, for children who specifically seek that kind of full-body pressure.

Movement-Based Calming Techniques

For children who respond better to movement, slow rhythmic input can be just as effective as deep pressure:

  • Slow rocking, whether in a chair, on a lap, or using a rocking toy.
  • Swinging at a steady, predictable pace, which combines movement with rhythm.
  • Walking at a steady pace, ideally somewhere with reduced visual and auditory clutter.

The key word is steady; fast or unpredictable movement tends to add sensory input rather than calm it, which is the opposite of what’s needed during overload.

Building a Calming Toolkit Before You Need It

The techniques above work best if they’re familiar to a child before a meltdown happens. A few ways to prepare in advance:

  • Identify go-to tools ahead of time. Our guide to sensory toys for autism covers specific product options organized by sensory type, useful for building out a toolkit before you need one.
  • Set up a dedicated calming space. A consistent, low-stimulation spot a child can retreat to makes a real difference. Our guide to home adaptations for autism covers how to set one up.
  • Practice the technique during calm moments, not just during overload, so it’s already familiar when you need it.

From In-the-Moment Calming to a Taught Self-Regulation Skill

In-the-moment calming is something a caregiver largely does for or with a child. Over time, many of these same techniques become something a child learns to recognize and use.

Our guide to self-management techniques for children with autism covers how that transition from caregiver-led to child-led calming typically happens.

This same regulation work matters directly for school readiness, too: a child who can recognize early overload signs and use a calming technique independently is far better equipped for a classroom day than one who can’t. It’s one of the specific skills built into Cardinal’s Classroom Readiness program, which practices these techniques in a structured group setting that mirrors an actual school day.

Ready to Build a Calming Plan for Your Child?

Every child’s sensory profile is different, and figuring out which calming techniques actually work takes some trial and error, ideally guided by someone who can watch a child’s specific responses and adjust from there.

Cardinal Pediatric Therapies helps families identify calming strategies that fit their child specifically, both for in-the-moment use and as a foundation for classroom readiness.

Contact our team to talk through what a calming plan could look like for your child.

What are good calming sensory activities for autism meltdowns? 

Deep pressure techniques a firm hug, weighted blanket, or compression vest and slow, rhythmic movement like rocking or swinging tend to be the most consistently effective in-the-moment options. The right technique still depends on the individual child.

Does deep pressure really help calm autistic children? 

Yes, there’s meaningful research support for this specifically. Reducing anxiety and arousal in children with autism, though individual response still varies from child to child.

How do I know if my child is close to a meltdown? 

Early signs usually include covering ears or eyes, increased stimming, pacing or restlessness, or sudden withdrawal. Learning your own child’s specific early pattern is usually more useful than following any general checklist alone.

Can calming sensory techniques be used at school?

Yes, many of the same techniques  fidget tools, brief movement breaks, a designated quiet space can be adapted for a classroom setting, though they typically need coordination with a teacher or aide. A classroom readiness program is one way to practice these skills in a group setting before school starts.

What’s the difference between a meltdown and sensory overload?

Sensory overload is the buildup of overwhelming input that precedes a meltdown, while a meltdown is the resulting loss of behavioral control once that buildup becomes too much. It’s generally far easier to calm a child before a meltdown is already underway.

Positive Reinforcement in ABA Therapy: Preparing Kids for the Classroom

Positive reinforcement means a child receives something motivating after a target behavior, making that behavior more likely to happen again. In early ABA therapy, that reinforcement is usually immediate and frequent: a token, praise, or preferred activity after nearly every success.

As a child moves toward classroom readiness, the reinforcement schedule has to change too.

Cardinal Pediatric Therapies builds that shift deliberately, rather than leaving a child to encounter it cold on the first day of school.

How Reinforcement Schedules Change as a Child Prepares for the Classroom

Early skill acquisition typically starts with continuous reinforcement, a reward after every single instance of the target behavior because it makes the connection between behavior and outcome as clear as possible.

Reinforcement procedures and schedules of reinforcement are core, tested competencies for behavior analysts under the Behavior Analyst Certification Board’s official Task List, and this shift from continuous to intermittent reinforcement, sometimes called schedule thinning is one of the core mechanics BCBAs use once a skill starts to stick.

For classroom-readiness goals specifically, that shift matters more than it might for a skill practiced only at home. A classroom teacher managing 15 or more students can’t reinforce every correct response the way a 1:1 RBT can, so a child whose reinforcement schedule is still dense when school starts is likely to struggle even on skills they’ve technically mastered in therapy.

At Cardinal, we’ve noticed that starting a token schedule ahead of time helps a lot with the transition to a classroom.

Token Economies for Classroom-Ready Skills

A token economy earning tokens for target behaviors, then exchanging them for a reward is one of the more common tools for bridging dense, immediate reinforcement toward the more delayed, intermittent reinforcement a classroom actually offers.

For classroom-readiness goals, token systems are often built around specific school-day skills:

  • Sitting through circle time without leaving the group
  • Waiting for a turn to speak or use a shared material
  • Following a multi-step instruction, the kind of skill our guide to task analysis in ABA therapy covers in more depth
  • Transitioning between activities on the group’s schedule rather than an individual one.

The token system itself typically starts intense: tokens earned frequently, exchanged quickly, and gradually stretches out as the underlying skill becomes more reliable, mirroring the reinforcement schedule shift happening underneath it.

Fading Reinforcement So Skills Hold Up Without 1:1 Support

The hardest part of classroom-readiness reinforcement work isn’t teaching the skill; it’s making sure the skill survives the move from a therapy setting to a classroom where reinforcement is naturally less frequent, less immediate, and less individualized.

A few things that help that transition hold up:

  • Practicing in a group setting before school starts, so a child experiences delayed and shared reinforcement before it matters for the first time on an actual first day.
  • Shifting from tangible rewards toward natural reinforcers praise, a preferred activity, social recognition since those are what a classroom can realistically sustain long-term.
  • Data-driven pacing, thinning the schedule based on how consistently a skill shows up rather than on a fixed timeline.

This is different work from simply reducing rewards across the board; reinforcement that’s faded too quickly can cause a skill to fall apart, while reinforcement kept too dense doesn’t prepare a child for what an actual classroom will look like.

What This Looks Like in Cardinal’s Classroom Readiness Program

Reinforcement schedule work like this is built directly into Cardinal’s Classroom Readiness program, which runs sessions structured like an actual school day: group instruction, transitions, and shared attention specifically so a child’s reinforcement schedule gets tested and adjusted in something closer to the environment they’re actually heading into, rather than staying dense in a 1:1 setting until the first day of school arrives.

If you’re looking for a more general explanation of what positive reinforcement is and how it works, including some of the common myths around reward-based teaching, our guide on the benefits of positive reinforcement in ABA therapy covers that ground in more depth.

Ready to Prepare Your Child’s Reinforcement Plan for School?

Every child’s reinforcement schedule needs a different pace of thinning, and getting it wrong in either direction too fast or too slow can undermine skills that otherwise looked solid in therapy. Our BCBAs build that plan specifically around each child’s classroom-readiness goals.

Contact our team to talk through what a reinforcement plan for the classroom could look like for your child.

What is positive reinforcement in ABA therapy? 

Positive reinforcement means a child receives something motivating immediately after a target behavior, which makes that behavior most likely to happen again.

How is positive reinforcement used to prepare a child for the classroom? 

Reinforcement schedules gradually shift from immediate and frequent to more delayed and intermittent, mirroring what an actual classroom can realistically provide. This shift, often practiced through token economies, will help a skill hold up once a child no longer has 1:1 immediate reinforcement available.

What is a token economy and how is it used in ABA? 

A token economy is a system where a child earns tokens for target behaviors and exchanges them for a reward once enough are collected. This is very different for each classroom-readiness goals, tokens are often tied to specific school-day skills like sitting through circle time or waiting for a turn.

Will a child become dependent on rewards from positive reinforcement?

The goal of reinforcement is actually the opposite: schedules are deliberately thinned over time so a skill becomes self-sustaining rather than reliant on constant rewards. Our guide on the benefits of positive reinforcement covers this and other common misconceptions in more depth.

How does reinforcement change once a child starts school? 

Reinforcement in a classroom is naturally less frequent, less immediate, and shared across many students rather than individualized.

Sensory Activities for Preschoolers with Autism

Preschool can be an overwhelming environment for our kids with autism: group noise, unpredictable transitions, fluorescent lighting, and long stretches of sitting still. 

For us, it’s important to have classroom sensory strategies, scheduled breaks, specific tools, and predictable routines to help a child stay regulated enough to participate, rather than spending the day in fight-or-flight mode.

This differs from general at-home sensory play and is usually built in partnership with a teacher, occupational therapist, and the Cardinal Pediatric Therapies ABA team.

Why the Classroom Triggers Different Sensory Challenges Than Home

At home, a child can usually retreat to a quiet room or take a break whenever they need one. A classroom doesn’t offer that same flexibility by default; a preschooler is expected to sit through circle time, transition between activities on the group’s schedule, and tolerate the noise level of ten or more other children in one room.

Some triggers that usually happen are: 

  • Circle time requires sitting still and attending for an extended stretch, which is difficult for a child seeking movement input.
  • Unpredictable transitions moving from centers to snack to outdoor play remove the structure and warning time a child may rely on to feel settled.
  • Group noise and overlapping voices are harder to filter out than the more controlled sound environment of home.
  • Shared materials and close physical proximity to other children can be overwhelming for a child sensitive to touch or personal space.

None of this means a classroom is a bad fit; it means the sensory support has to be built into the classroom routine itself, not just practiced at home and expected to transfer automatically. For general at-home sensory play ideas by sensory type, our sensory activities guide covers tactile, proprioceptive, and vestibular activities in more depth.

Sensory Tools That Work During the School Day

Some classroom-friendly strategies  that we have noticed make a difference are:

  • Scheduled movement breaks: a short walk, chair push-ups, or a few minutes at a wall push station can help prevent meltdowns.
  • Fidget tools during seated time: a small fidget or stress ball during circle time can provide enough input to help a child stay seated and attentive.
  • Weighted lap pads: light, calming pressure during seated work, without removing the child from the group setting.
  • Noise-reducing headphones: these are useful during loud transitions like assemblies, fire drills, or lunchroom noise.
  • Designated quiet corner: a small, low-stimulation space in or near the classroom where a child can take a short reset without leaving the room entirely.

The goal isn’t to eliminate every sensory trigger that’s not realistic in a group classroom, but to give a child predictable tools to manage the ones that come up most often.

Building Sensory Support Into Classroom Routines

Sensory strategies work best when they’re anticipated. A few ways our  teams build that into a daily routine:

  • Visual schedules that show what’s coming next, so transitions aren’t a surprise.
  • Warning cues before transitions: a timer, a song, or a verbal countdown a few minutes before a change in activity.
  • Breaks timed before known trigger points,  scheduling a movement break right before an assembly or a loud group activity.
  • Consistency between settings: when the sensory tools and language used at home, in therapy, and in the classroom match, a child doesn’t have to relearn the system in each place.

This kind of planning works best with input from everyone involved: the classroom teacher, an occupational therapist if the child has one, and the ABA team, so accommodations are consistent rather than conflicting. It’s the same kind of cross-setting consistency our guide to ABA therapy in schools covers in more depth.

It’s worth noting that the research on formal sensory integration therapy specifically is still developing. A 2018 systematic review found moderate evidence that occupational therapy using Ayres Sensory Integration, a specific, structured protocol delivered by a trained OT, produces positive outcomes for children with autism.

 A separate 2018 review looking at individual sensory techniques used on their own, such as weighted vests or incorporating sensory activities into preschool routines, found much weaker evidence: limited support for weighted vests and insufficient evidence for classroom-style sensory routines specifically. In practice, that’s exactly why classroom sensory strategies tend to work best as one part of a broader, individualized plan rather than a substitute for it.

How This Connects to Classroom Readiness

Practicing sensory regulation in a real group setting before the first day of school is a core part of what a classroom readiness program is designed to do.

Cardinal’s Classroom Readiness program runs sessions structured like an actual school day: circle time, group instruction, and transitions between activities, which gives a child the chance to practice using sensory tools and breaks in the exact kind of setting where they’ll need them, with a BCBA adjusting the plan based on how the child actually responds.

Ready to Talk Through Your Child’s Classroom Needs?

Every child’s sensory profile looks different in a classroom setting than it does at home, which is why sensory accommodations work best when they’re built specifically for the school environment your child is heading into. 

Our team incorporates sensory strategies directly into the Classroom Readiness program described above.

Contact our team to talk through what classroom sensory support could look like for your child.

What are sensory strategies for a preschooler with autism in the classroom? 

Scheduled movement breaks, fidget tools during seated time, ear defenders, and a designated quiet corner are common classroom-friendly strategies. The right combination depends on the child’s specific sensory profile, the classroom’s layout, and how the teacher structures the day.

How often should sensory breaks happen during a school day?

There’s no universal number; it depends on the child and the classroom schedule. Many teams start by placing breaks before known demanding activities.

What sensory tools are commonly allowed in preschool classrooms?

Small, quiet fidget tools, weighted lap pads, and noise-reducing headphones are commonly used in preschool settings without disrupting other children.

Is sensory integration therapy an evidence-based practice for autism?

The evidence is mixed. A 2018 review found moderate support for structured Ayres Sensory Integration delivered, while a separate 2018 review of standalone techniques like weighted vests found much weaker evidence and generally recommended sensory work as one part of a broader plan.

How do I ask my child’s preschool teacher about adding sensory accommodations?

Start with specific, concrete requests: a fidget during circle time, a warning cue before transitions, or a quiet corner option. This will help them provide more personalized accommodations.

Task Analysis in ABA Therapy: How It Works

Task analysis is the process of breaking a complex skill into smaller, teachable steps. Skills that look automatic to an adult, washing hands, packing a backpack, lining up for recess, are actually made up of many small actions performed in order. 

In ABA therapy, our behavior analysts identify each step, then the team teaches them one at a time until the child can complete the full skill independently. It’s one of the most widely used tools in behavior analysis, and our BCBAs at Cardinal Pediatric Therapies rely on it throughout classroom readiness goals.

What Task Analysis Looks Like in ABA Therapy

When behavior analysts call the finished skill a “terminal behavior,” it’s the full routine once every step is mastered. Before teaching begins, our team maps out every individual action required to get there. Putting on a shoe, for instance, isn’t one step; it’s picking up the shoe, sliding it on, and fastening it; each small action becomes its own teaching target.

Once the steps are mapped, our team assesses which ones the child can already do and which ones need direct teaching. The step-by-step data lets a BCBA adjust the plan in real time rather than guessing what’s working; it’s also how progress is measured in a classroom readiness program.

How Task Analysis Connects to Chaining

Task analysis identifies the steps; chaining is how those steps actually get taught and linked together. The three main chaining methods are:

  • Forward chaining: the child learns the first step first, then the second, building the sequence from the beginning.
  • Backward chaining: the child learns the last step first, so they experience finishing the task successfully from the very first session.
  • Total task chaining: the child practices the entire sequence each time, with support at whichever steps they haven’t mastered yet.

Which method a BCBA chooses depends on the skill and the individual child; there’s no single “correct” chaining method, only the one that fits the goal. Once a child masters a chained skill in a therapy setting, generalizing it to an actual classroom is its own separate process, which our guide to ABA therapy in schools covers in more depth.

Task Analysis for Classroom Readiness Skills

Many of the skills that determine whether a child’s first weeks in a classroom go smoothly aren’t academic at all; they’re multi-step routines that task analysis is especially well suited to teach:

  • Transitioning between activities: putting away one material, moving to a new area, and starting a new task without a meltdown.
  • Following a visual schedule: checking the schedule, identifying the next activity, and moving to it independently.
  • Lining up and waiting: recognizing the cue to line up, finding a spot, and waiting without leaving the line.
  • Raising a hand and waiting to be called on: a short sequence that’s easy to overlook but genuinely made up of distinct steps: noticing the urge to speak, raising a hand instead, and waiting.
  • Packing and unpacking a backpack:  putting away morning items, retrieving what’s needed for the next activity, and repeating the reverse process at the end of the day.

These are exactly the kinds of routines targeted in Cardinal’s Classroom Readiness program, which structures sessions to mirror an actual school day: circle time, group instruction, and transitions between activities so the skills practiced in therapy transfer directly to a real classroom.

Why Task Analysis Is Considered an Evidence-Based Practice

Task analysis is one of the evidence-based practices recognized by the National Professional Development Center on Autism Spectrum Disorder, based on a systematic review of the research literature conducted by the National Clearinghouse on Autism Evidence and Practice. 

That review found that task analysis meets evidence-based practice criteria based on the studies examined and identified it as a “focused intervention,” meaning it’s typically combined with other strategies like prompting and reinforcement rather than used entirely on its own. In practice, that means task analysis rarely stands alone in a session; it’s paired with prompting, time delay, or reinforcement to teach each step once it’s identified.

Building Classroom Skills Step by Step

Every skill on a classroom readiness goal list, from lining up to following a multi-step instruction, can be broken into smaller steps a child is actually ready to learn.

At Cardinal Pediatric Therapies, task analysis is one of the tools our BCBAs use throughout the Classroom Readiness program to build the routines kids need before their first day.

Contact our team to talk through what a task analysis approach could look like for your child.

Frequently Asked Questions

What is task analysis in ABA therapy? 

Task analysis is the process of breaking a complex skill into a sequence of smaller, teachable steps. It’s used to teach multi-step routines like getting dressed, following classroom transitions, or completing a morning arrival routine, one manageable piece at a time.

What’s the difference between task analysis and chaining? 

Task analysis identifies and sequences the individual steps of a skill; chaining is the teaching method used to link those steps together. You can’t do chaining without a task analysis first, since chaining requires already knowing exactly what the steps are.

How does task analysis help prepare a child for kindergarten or preschool?

Many classroom routines lining up, following a visual schedule, packing a backpack, transitioning between activities are multi-step skills that task analysis breaks into learnable pieces. This lets a child build classroom stamina gradually, rather than being expected to master an entire routine all at once.

What is an example of a task analysis?

Washing hands is a common example: turning on the water, wetting hands, applying soap, scrubbing for a set time, rinsing, and drying, each treated as its own teachable step. A classroom example might break “lining up for recess” into recognizing the cue, standing, walking to the line, and waiting.

Is task analysis only used with young children?

No. Task analysis applies to self-care skills, academic tasks, vocational skills, and social routines across a wide age range, from early childhood through adolescence. The specific skills and number of steps change based on the learner’s goals, but the approach itself is used well beyond early classroom readiness work.

Transitioning to Kindergarten with Autism

Transitioning to kindergarten with autism brings up a specific kind of worry, not just “will my child be okay,” but “am I doing enough right now to actually get them ready.” 

Alice Okamoto, MA, BCBA, LBA and Chief of Staff at Cardinal Pediatric Therapies, breaks down what actually predicts a smooth start, the delay-versus-start question parents ask more than any other, and one thing you can practice at home today.

 Academics vs. Group Skills: What Predicts a Smooth Start

Most families spend the summer before kindergarten on letters, numbers, maybe some writing practice. That’s not wasted time, but it’s not where the real risk sits.

What most families focus onWhat actually predicts a smooth start
Letters, numbers, early writingFollowing an instruction in a group of 20
Reading readinessWaiting a turn without escalating
Counting and shapesHandling a transition nobody warned them about

“The thing that actually trips kids up in September is not having practiced being in a group,” Alice says. Those group skills take repetition, and repetition takes time. A family starting to think about it in August is already working with a tight window. Our page on academic success for children with autism goes deeper on the academic side specifically, but that piece isn’t the one that predicts September.


What Kindergarten Teachers Expect on Day One

The bar isn’t what most people assume.

“They expect independence with routine stuff,” Alice explains, “hanging up a backpack, finding a seat, following a two- or three-step direction without it being repeated five times.” Teachers know day one is chaotic for every child in the room. 

What they’re watching for is whether a child can function inside a group without one-on-one support next to them, which is exactly the structure our classroom readiness program is built around.

Not sure whether your child is closer to ready than you think, or further than you’d like? That’s a conversation worth having before the school year, not after. Reach out here, and we’ll talk through where your child actually stands.

Common Mistakes Parents Make Preparing for Kindergarten

None of these come from doing something wrong. They’re instincts that make sense everywhere else in parenting, just applied somewhere they don’t quite work the same way.

InstinctWhy it backfiresWhat works instead
Rehearsing one exact morning routineTeaches a script, not a skill. A fire drill or substitute breaks it instantlyPractice handling change itself, in different contexts
Waiting to start group-skill prepLeaves little runway once academics feel “handled”Start group and transition practice early, alongside academics
Telling the teacher too lateTeacher learns your child’s needs through trial and errorShare communication style and triggers before day one
Judging by a rough first weekOne hard week isn’t a signal it’s failingExpect an adjustment period, most kids have one

Handling Schedule Changes and Transitions

Kindergarten schedules look consistent on paper and rarely are in practice: assemblies, substitutes, fire drills, an unannounced field trip. That unpredictability is exactly where a lot of autistic kids struggle most.

“What we work on is building the skill of transitioning itself, not memorizing one specific schedule,” Alice says. A few things that help:

  • A visual timer or a warning before a change happens
  • Naming what’s coming next, not just announcing “it’s time to stop”
  • Practicing transitions in several different settings, not the same three at home
  • Reinforcing the transition itself, not just the new activity

If a child learns “when I hear this signal, something is about to change, and that’s okay,” that skill travels with them no matter what the day looks like.

Delay Kindergarten, or Start With More Support?

The question Alice gets asked more than any other, and it doesn’t have one right answer.

Delay might help whenDelaying likely won’t help when
The gap is mostly about age and general maturityThe gap is specific skills that need direct teaching
More time would let skill-building actually happenNothing structured is planned for that extra year
The child is close, just needs a few more monthsWaiting just delays the same problem by a year

“It depends on where the child actually is, not their age on paper,” Alice says. This is a decision worth making with a clinician who knows your child, not a blanket rule either direction.

The National Association for the Education of Young Children makes a similar point for families broadly: readiness is about the whole child’s skills, not a single test or a birthday.

One Skill to Practice at Home Today

If you only do one thing before school starts, Alice has a specific answer: practice following a two-step instruction in a distracting environment.

  1. Pick something small, not “clean your room.” Try “put your cup in the sink, then come sit down.”
  2. Do it with real distraction present, the TV on, a sibling being loud.
  3. Give the instruction once. Don’t repeat it five times.
  4. Reinforce immediately when your child follows through.

“That’s basically what a classroom is, instructions given once, with plenty of noise and distraction around,” Alice says. If a child can do that reliably at home, it transfers straight into the classroom.

For more structured activity ideas in this category, our article on preschool classroom activities for kids with autism has exercises you can start this week.

Should I tell my child's kindergarten teacher about their autism diagnosis 

Kindergarten Support at Cardinal

Most families who talk to us about kindergarten are somewhere in the middle: not in crisis, not fully confident, just unsure whether what they’re doing at home is enough.

Our program builds the specific group skills a kindergarten classroom will ask for, following instructions, communicating without heavy support, initiating play with peers, handling transitions, inside small groups structured to mirror an actual school day.

It’s one part of the full range of ABA therapy services we provide, and every plan accounts for where your child is right now, not a generic script.

Frequently Asked Questions

At what age should autism-focused kindergarten preparation start? 

There’s no single age that works for every child, since readiness is based on specific skills rather than a birthday. Many families begin focused preparation, especially in group and transition skills, six months to a year before the expected start date. 

What skills matter most for kindergarten readiness with autism? 

Following instructions without repetition, handling transitions, communicating needs, and functioning inside a group without one-on-one support tend to matter more than early academic skills, which most children pick up once they’re settled into the classroom routine. 

Should I tell my child’s kindergarten teacher about their autism diagnosis? 

Most educators recommend sharing relevant information before school starts, including diagnosis, communication style, and what helps at home. This gives the teacher a head start rather than learning through trial and error during the first weeks.

How long does it typically take for an autistic child to adjust to kindergarten? 

It varies widely. Some adjust within the first few weeks; others take a full semester, particularly if group and transition skills weren’t practiced beforehand. Consistent routines at home and school tend to shorten the adjustment period.

What is the biggest mistake parents make preparing for kindergarten?

Focusing mainly on academics. As Alice puts it, letters and numbers matter, but the skill that actually predicts a smooth start is functioning in a group, following instructions, and handling transitions without one-on-one support.

Preschool Classroom Activities for Kids with Autism

If you’re looking for preschool autism classroom activities, you probably want more than a generic list; you want activities that actually build the skills your child will need once they’re sitting in a real classroom. 

Below are practical, play-based activities organized by the skill each targets, along with the reasoning behind why they work, based on the same ABA principles Cardinal uses in our classroom readiness program.

Why These Specific Skills, and Not Just “Fun Activities”

A lot of activity lists online are really just fun ideas with autism attached as a label. These are different. Each one below is built around a specific classroom skill: communicating without a meltdown, taking turns without a fight, moving from one activity to the next without shutting down. 

Those are the skills that predict how smoothly the first weeks of school actually go, more than knowing colors or shapes. 

Our article on what a classroom readiness program actually is goes deeper into how these skills are formally built, but you can absolutely start practicing them at home.

Communication Activities

ActivityWhat it builds
Choice boards at snack time, “do you want crackers or grapes”Requesting wants without frustration, a foundational classroom skill
Narrating play out loud as you play alongside your childModeling language your child can borrow and reuse
“First, then” visual boards for any two-step activityPredictability, which reduces the anxiety that often triggers meltdowns
Simple call-and-response songs with a pause for your child to fill in the wordLow-pressure verbal participation in a group format

Start small. A choice between two things is a communication opportunity even if your child only points. The goal is participation, not perfect sentences.

Turn-Taking and Group Play Activities

  • Rolling a ball back and forth. About as simple as it gets, and it’s a real turn-taking rep every single time.
  • Building a tower together, one block at a time. Forces a wait, which is exactly the skill a circle time or group activity will ask for.
  • Board games with an obvious visual turn marker. A spinner or a “my turn” card removes the ambiguity that causes most turn-taking conflicts.
  • Parallel play with a shared bin of toys. Not every group skill starts with direct interaction. Sitting near another child doing a similar activity is a real, valid first step.

Following Instructions and Transition Activities

Transitions are where a lot of preschool mornings fall apart, and they’re also one of the most trainable skills on this whole list.

Practicing instructions

Start with one-step instructions that your child already reliably follows (“give me the cup”), and reinforce them immediately. 

Once that’s solid, move to two-step (“put the cup on the table, then sit down”). This is the same building-block approach, called task analysis, that a BCBA uses to design any new skill, breaking it into pieces small enough to succeed at consistently.

Practicing transitions

  • Use a visual timer or a 5-minute warning before switching activities
  • Give the next activity a name your child can anticipate, “next we’re doing puzzle time,” not just “okay, time to stop”
  • Practice small transitions at home first, snack to playtime, before expecting a smooth transition in a group setting
  • Reinforce the transition itself, not just the new activity. A quick “you switched activities so fast!” matters

A Note on Sensory Play

Sensory activities are a huge and genuinely important category on their own, things like textured bins, movement breaks, and calming tools. We’ve covered that ground separately in our article on sensory activities for preschoolers with autism, so we kept this list focused on communication, turn-taking, and transitions instead of overlapping with it.

How Cardinal Builds on These Activities

The activities above are genuinely useful on their own, and many parents see real traction just from consistent practice at home. What a classroom readiness program adds is structure, repetition, and a trained set of eyes noticing exactly where a specific child gets stuck.

Our classroom readiness program runs these same categories of skills: communication, turn-taking, transitions, following group instruction- inside a group setting that mirrors an actual classroom, with a BCBA tracking what’s working and adjusting the plan as your child progresses. 

If home practice feels like it’s plateaued, or you want a clearer read on where your child actually stands, that’s exactly the kind of thing worth a quick conversation. 

Reach out here, and we’ll talk through what would help most.

Frequently Asked Questions

What activities help autistic preschoolers with transitions? 

Visual timers, verbal warnings before a switch, and naming the next activity in advance all help. Practicing small transitions at home, like moving from snack to playtime, builds the same skill needed for bigger classroom transitions later.

How can I help my nonverbal preschooler participate in group activities? 

Parallel play, choice boards, and physical participation in games like rolling a ball all count as real participation, even without spoken language. The goal is inclusion in the activity, not verbal output, and communication support can build alongside it. 

What is task analysis in ABA therapy? 

Task analysis means breaking a skill into small, sequential steps a child can succeed at one at a time, rather than expecting the whole skill at once. It’s the same method used to teach anything from following instructions to getting dressed independently. 

How many classroom-type activities should we practice at home each week? 

There’s no fixed number. A few short, consistent sessions, five to ten minutes, several times a week tend to work better than one long session. Consistency and immediate positive reinforcement matter more than duration. 

Why does play-based learning work better than table-based drills for some kids? 

Not every child learns best at a table. As Cardinal’s team puts it, much of therapy is naturalistic, meaning skills are taught through play, on beanbags, or in whatever setting the child is already engaged in, rather than just seated instruction. 

ABA Therapy in Schools: What It Actually Means for Your Child

If you’re searching for ABA therapy in schools, you’re probably picturing a therapist sitting with your child at their desk every day. That’s one version of it, and it isn’t what every family actually needs, or has access to. 

Here’s what the term usually means, some real numbers on how common these services actually are, and the specific way Cardinal helps children get genuinely ready for a classroom instead.

What “ABA Therapy in Schools” Usually Means

When people search this term, they’re typically picturing a therapist embedded in their child’s actual classroom, working alongside the teacher during the school day. 

Some providers do offer that. Whether it’s available to your family usually depends on insurance approval, school district policy, and whether the school agrees to let an outside provider into the building, and that last part varies enormously from district to district. No provider can promise it up front, no matter what their website says.

There’s also a completely separate, school-run version of this: related services delivered through your child’s IEP, governed by IDEA, the federal law requiring public schools to support students with disabilities. That system is run by the school, not by a private ABA provider like Cardinal, and understanding the difference matters before you spend time searching for a provider to “come to school.”

ABA Therapy in Schools

The two systems, side by side

Private ABA therapySchool-based services (IEP)
Who delivers itA private provider like CardinalThe school district’s own staff
Who paysInsurance or private payThe public school system, at no cost to you
Who sets the goalsA BCBA, based on clinical assessmentAn IEP team, including you, teachers, and school specialists
Can they work togetherYes, with coordination between both teamsYes, this is common and often recommended

Real Numbers on How Common This Is

You are not dealing with something rare. Nationally, more than 882,000 students had an IEP specifically because of autism in the 2021-22 school year, up from roughly 93,000 just two decades earlier, and autism now accounts for more than 12% of all IEPs in the country, according to federal data. Separately, the CDC estimates autism now affects roughly 1 in 31 children by age 8.

What that means practically: your child’s school has almost certainly worked with autistic students before, has some familiarity with IEP-based supports, and your questions are not unusual ones for them to field. That doesn’t mean every school gets it right, but it does mean you’re not the first family to ask.

What Cardinal Actually Offers Instead

Cardinal doesn’t place therapists inside public school classrooms on a daily basis. What we do instead is build the skills your child needs to succeed in that classroom before they’re in it, and stay involved once they are.

What families often pictureWhat Cardinal actually provides
A therapist sitting in class dailyA clinic-based classroom readiness program that mirrors real classroom structure
Therapy delivered inside the school buildingIn-home ABA therapy, with sessions that can extend into daycare or community settings tied to specific goals
No contact between provider and schoolCoordination with your child’s teachers and school staff during the transition

Alice Okamoto, Cardinal’s Chief of Staff, began her career in ABA within a school setting and has worked across schools, homes, and clinics since. That background shapes how this program is built: the goal was never to replace the classroom; it’s to make sure a child walks into one already able to handle what it demands.

Classroom Readiness: The Bridge We Actually Build

This is where most of the real work happens. Our classroom readiness program runs in clinic, in small groups of up to ten children, structured to feel like an actual school day: circle time, group instruction, transitions between activities.

The specific skills it targets

  • Following group instructions, not just one-on-one direction
  • Communicating wants and needs without heavy adult support
  • Initiating play with peers, independently or with minimal prompting
  • Handling transitions between activities without escalating
  • Tolerating group expectations, waiting a turn, staying with the group

Those are the same skills that determine whether a child’s first weeks in an actual classroom go smoothly, far more than whether they know their letters and numbers. If you want the full breakdown of who the program is for and what a session looks like, our article on what a classroom readiness program actually is covers it in depth.

Wondering whether classroom readiness or a different starting point makes more sense for your child? That’s exactly the kind of thing a quick conversation can sort out. Reach out here, and we’ll walk through it with you.

Questions Worth Asking Before Your Child Starts School

Whether you’re working with Cardinal, your school district, or both, these are worth having answers to before the first day:

  1. Does my child qualify for an IEP or a 504 plan? These are different, and eligibility criteria differ. Ask the school to explain both.
  2. What related services would the school actually provide? Speech, OT, and behavioral support are common, but availability varies by district and by staffing that year.
  3. Has my child’s teacher worked with autistic students before? Not disqualifying if the answer is no, but it tells you what kind of support and training conversation you’ll need to have.
  4. Can our private provider share information with the school team? With your consent, most can and should. Ask both sides directly rather than assuming.
  5. What does a typical day actually look like for my child? Ask for specifics, transition times, group size, sensory environment, not just general reassurance.

How We Coordinate With Your Child’s Actual School

Even though we’re not placing a therapist in the building, we don’t disappear once your child is enrolled either. Cardinal’s Arizona program confirms that families receive support for children transitioning to school settings, including coordination with teachers and school staff, and that same approach guides how our teams work with families more broadly.

What that coordination actually looks like

  • Your BCBA can share relevant progress information with your child’s school team, with your consent
  • We answer questions from teachers or school staff about strategies that are working at Cardinal
  • We help make sure the skills your child is building here stay consistent with what’s expected in their classroom

This isn’t a substitute for your child’s IEP team or their school-provided related services. It’s a second set of eyes working from the same picture, rather than two disconnected ones. 

And because a lot of the skills a classroom needs- communication, following routines, generalizing across settings- are the same ones we build through in-home ABA therapy, progress your child makes at home tends to travel with them into the classroom.

Frequently Asked Questions

Does ABA therapy happen inside public schools? 

Sometimes, depending on the provider, insurance approval, and the school district’s policies, which vary widely. Some ABA providers place therapists directly in classrooms. Others, including Cardinal, focus on preparing children for the classroom through clinic-based programs and close coordination with school staff instead.

What is the difference between ABA therapy and school-based related services? 

ABA therapy is typically delivered by a private provider and funded through insurance or private pay. School-based related services, like speech or OT delivered through an IEP, are provided by the school itself under IDEA and are separate systems that can work alongside each other.

Can my child get ABA therapy and an IEP at the same time? 

Yes. Many children receive ABA therapy from a private provider while also having an IEP through their school. The two are developed by different teams for different purposes, and coordination between them, sharing progress, aligning goals, tends to produce the most consistent results. 

How do I know if my child needs classroom readiness support before starting school? 

If your child struggles with transitions, group instruction, or being around peers without one-on-one support, a BCBA can assess whether classroom-specific preparation would be helpful before enrollment. This is distinct from general developmental delay and warrants direct evaluation by a provider.

How does Cardinal work with my child’s school team? 

During intake, families are asked whether their child receives related services such as speech or OT, and release-of-information forms allow Cardinal’s team to coordinate directly with those providers. It’s the same collaborative approach that extends to teachers and school staff during a child’s classroom transition. 

Dr. Mike Henderson, Ph.D., BCBA-D, LBA

Regional Operations Director

North Carolina

Mike Henderson, PhD, LBA, BCBA-D, is the Regional Operations Director at Cardinal Pediatric Therapies. With over two decades of experience in behavior analysis and organizational leadership, he focuses on mentoring teams and fostering a culture of collaboration, growth, and excellence in client care. Mike believes strong leadership and supportive systems are essential for helping clients, families, and providers succeed together.

Felicia Freeman

Clinic Manager

I am Felicia Freeman, the Clinic Manager for Cardinal Pediatric Therapies. I have been in ABA for several years now and am passionate about the community that we serve. I started out as an RBT, decided to go the administrative route, and worked my way up to managing clinics. I choose this field every day because I enjoy making a meaningful impact in the lives of our clients and building strong teams that change lives.

Amanda Dean, MA, BCBA, LBA

Johnston County, NC

Amanda graduated from The Chicago School of Professional Psychology in 2018 with her Masters in Psychology. She proceeded to complete her graduate certificate in ABA and became a BCBA in November 2020. Amanda has a passion for behavior reduction, tolerance training and functional communication training. She enjoys spending as much time as she can with her 3 children and husband. When she’s not working, Amanda is very involved in her local Pop Warner Cheerleading program where she is the Assistant Cheer Director and a head coach.

Becky Fronheiser

Operations Director

Arizona

Becky has worked in behavioral health for 7 years. She joined Cardinal in the spring of 2024.  Becky is grateful for the opportunity to work with such a passionate group of people and looks forward to supporting families with their specific ABA needs.  In her personal time, she enjoys spending quality time with her husband, 6 kids and 4 grandkids and loves to travel and relax on the beach.

Matthew Wilkinson

Operations Director

Cary, NC

Matthew holds a bachelors degree from the University of Utah, Medical Degree from the Autonomous University of Guadalajara and an MBA from Western Governors University. He has worked in the pediatric field for the majority of his professional life and has a passion for helping bring the best care to children in need. He enjoys spending time with his wife and three children and day trips to the coast.


Trisha Iannotta Bieszczad, PsyD., BCBA

Triad, NC

Trisha is a Board Certified Behavior Analyst (BCBA) with extensive expertise since 2016 in applying behavior analytic principles to improve the lives of children and adolescents. Her professional journey began with a doctoral degree in clinical psychology, emphasizing child and adolescent development. This foundation has equipped her with a deep understanding of psychological theories and practices, which she seamlessly integrates into her work as a BCBA. Outside of her professional endeavors, Trisha enjoys reading, spending time outdoors with her family & trying out new restaurants. Trisha’s dedication to both her career and personal interests reflects her commitment to continual growth and enrichment, both professionally and personally. Her multifaceted background allows her to approach each aspect of her life with a blend of expertise, enthusiasm, and a genuine appreciation for learning and exploration.

Tina Lee

Director of Finance

Tina Lee is the Finance Director for Cardinal with a variety of experience in the Healthcare Industry for over 13 years. She is compassionate and always eager to assist where she can. In the ever-changing Healthcare environment, Tina has played a vital role in putting processes in place to obtain high efficiency outcomes to help our clients get the care they need. Tina enjoys the outdoors and loves spending time with her family.

William Evans

Director of Outreach and Recruitment

William is a UNCW Graduate who started his professional career working in Marketing and Recruiting for a local technology company before looking for an opportunity to take those skills and help others. In his spare time he plays hockey, including annually for the North Carolina Autism Hockey Tournament, which is dedicated to the raising money and awareness for organizations helping local families with children diagnosed with autism.

Alice Okamoto, MA, BCBA, LBA

Chief of Staff

Alice has been with Cardinal for over 4 years and has worn many hats along the way!  Alice has a passion for working with clients and families as a unit, supervising behavior analyst trainees, and collaborating on strategic initiatives to ensure clinical efficiencies.  Alice‘s professional experience began with ABA in a school setting, and has worked in schools, homes, and clinics throughout the years while enjoying collaboration with related providers.  In her free time, Alice enjoys traveling, exploring parks with her dog, Oliver, and trying new restaurants. 

Darrin Miller

CEO

Darrin has dedicated his education and career to the field of behavioral health. As a licensed therapist and master’s in clinical counseling he works to create solutions that improve the lives of those impacted by Autism Spectrum Disorder at a local, state, and national level. He strives to create a culture of caring and empathy while innovating solutions for improving families’ access to quality care as quickly as possible.